
INTRODUCTION
Stroke, spinal cord injuries, other neurological diseases, or aging are among the main causes of disability and limitation in everyday activities, including those related to the lower limb [1,2]. Gait disorders affect around 60% of patients with neuromuscular conditions and significantly reduce quality of life. Limited mobility often leads to a sedentary lifestyle, increasing the risk of secondary health issues like cardiovascular problems, obesity, and pressure ulcers, which can shorten life expectancy. As a result, restoring abilities enabling performing activities of daily living, including walking, is a key rehabilitation goal [3].
Physiotherapy is one of the fundamental procedures for improving a patient’s functional condition. It applies to both direct damage to the musculoskeletal system and damage to the nervous system, which indirectly affects musculoskeletal function [4-8]. In cases of musculoskeletal injury, physical rehabilitation focuses on strengthening muscles and improving joint mobility. In contrast, for nervous system damage, rehabilitation relies on a phenomenon known as neuroplasticity. Neuroplasticity supports improvements in daily functioning, enhances functional abilities, and fosters independence [9]. Rehabilitation enables structural changes in neural tissue, such as remyelination, neuroaxon regeneration, neuronal sprouting, and synaptogenesis, as well as functional changes that reflect adaptive reorganization of neural networks [10].
A growing number of robotic devices are being developed to support the described processes [11,12]. These technologies allow for more individualized therapy tailored to the patient’s specific needs and impairments, enhance motivation, and enable a higher number of precise repetitions [13,14]. Such devices can benefit the healthcare system broadly, not only by improving patient outcomes, but also by supporting and reducing the workload of physiotherapists. Moreover, they facilitate the collection of objective data and precise measurements, contributing to more accurate monitoring of rehabilitation progress [15].
Currently, task-oriented therapy can be delivered aided by robotic systems. This approach is well-supported by scientific evidence and has shown strong therapeutic outcomes in patients [16]. In general, the task-oriented exercising remains an effective rehabilitation method that emphasizes high-intensity, repetitive practice of activities that are meaningful and relevant to the patient, with a client-centered focus [9,15].
Despite growing awareness of the benefits of physiotherapy, access to rehabilitation services remains limited for many individuals. Barriers such as a shortage of specialists, transportation difficulties, or living in remote areas often prevent patients from receiving appropriate care. Additionally, high demand for physiotherapy can lead to long waiting times, which can lead to complications and longer therapy required [17]. In such cases, where rehabilitation is needed but not readily available, telerehabilitation offers a promising solution by improving access to services and reducing the burden on the healthcare system [8,18]. However, the tools for constant personalisation and safety monitoring, as well as for the teleoperation over robotic devices providing therapy, are not ready yet [11,13]. Modern telerehabilitation is in the process of evolving beyond simple phone consultations or video calls. Advanced technologies, such as biomedical sensors, are being introduced to provide biofeedback, allowing patients to adjust exercise difficulty based on their capabilities and current health status [19]. However, there is a large scientific gap in this field.
SmartEx-Twin project corresponds to these needs. The approach was based on the key insights regarding state of the art and technology readiness for the application, including:
minimally supervised robot-aided rehabilitation can result in increased therapy doses, critical for restoring motor capabilities of patients, while reducing workloads on the healthcare system [20];
to make the therapy more accessible for people with various motion limitations, it can be provided in a home-like environment as telerehabilitation service - for the robot-aided treatment, the devices should be fully controllable remotely, possibly with the technology of the digital twin to visualize the current state to the operator [18,21];
robotic rehabilitation has the potential to provide more precise personalization of treatment and improved supervision of the rehabilitation process. Integration of motion and biomedical signal tracking, such as electromyography (EMG) and electroencephalography (EEG), enables complex monitoring of performance along with safety [22-25], and even optimizing the effectiveness of the therapy [26] or be implemented directly in control of the devices [27].
The SmartEx-Twin exoskeleton-based system provides physical support within task-oriented exercising of the lower extremity. Due to the mentioned insights, it enables automation of treatment in a home-like environment. Thanks to integrating it with EMG and EEG tracking, the system is capable of intelligently maximizing patients' performance with the human-in-the-loop concept [28] and monitoring their safety [29]. The device is set to assist in repeating motions initially, one-time recorded by a physiotherapist, and adjust the assistance based on the correctness of the muscular activity assessed for the actual motions. Additionally, the EEG system is used to estimate the emotional state of a patient, with a particular focus on strain and discomfort. The former is considered the desired state for challenging exercises, while the latter is treated as the pre-pain state. The safety system of the device combines the possibility of manual immediate stop and the automatic stop based on EMG and EEG tracking. This includes detecting a constant discomfort state or excessive speed of muscle contraction, which can be a signal for spastic-related muscle cramps or spasms [30]. To provide maximum safety to the patient [31], the system is deactivated prior to the occurrence of hazardous situations. As the therapy may be only monitored over distance, the physiotherapist is capable of undertaking actions in case of an emergency stop. With the system's digital twin in virtual reality (VR), they can teleoperate the device to record the new motion trajectory and restart exercising in a safe way for patients [18,32]. While teleoperating the system, a specialist can constantly monitor the current configuration of the physical device, the emotional state of a patient, and the muscular activity based on tracking systems. In this work, the term 'intelligent algorithms' refers to a class of computational-intelligence methods, including related data-driven techniques and fuzzy logic, applied to biosignal processing and control; it does not imply autonomous decision-making, which remains determined by the implemented structure.
Compared to existing lower-limb rehabilitation exoskeletons and robotic gait trainers (e.g., Lokomat, Ekso Bionic, ReWalk or HAL), which typically operate under constant on-site physiotherapist supervision and provide limited biofeedback, the SmartEx-Twin system distinguishes itself in three key respects. First, it employs real-time EMG-based correction of assistive torque during the exercise itself, rather than only assessing performance post-hoc. Second, EEG-derived emotional state information is used both to maximise therapeutic challenge (strain detection) and to ensure patient safety (pain prediction), a combination not reported in prior lower-limb exoskeleton studies. Third, the VR digital-twin interface enables a remote physiotherapist to re-programme and restart therapy following an automated safety stop, without the patient leaving the home environment. This combination of features directly addresses the gap between technology readiness and clinical home-use requirements identified in recent systematic reviews [11].
This study aims to validate the effectiveness of the proposed intelligent treatment algorithms, teleoperation via the VR digital twin, and innovative safety systems based on EMG and EEG. For this reason, the investigation includes tests on humans to prove the set of hypotheses presented in section 2. Proving the effectiveness will enable bridging the cutting-edge technology of advanced rehabilitation exoskeletons with the need for safe home use and high-dose precision medicine.
METHODOLOGY
The experiments were performed on a heterogeneous group of 35 volunteers, including healthy participants and patients with medical conditions. The age distribution and experimental population shares regarding medical conditions are visualised in Figure 1. Both these factor combinations cover the whole range of considered individual cases within the experimental plan accepted by the bioethical committee. The experimental group was intentionally heterogeneous, encompassing participants with neurological, orthopaedic, cardiological, and no precisely diagnosed conditions, to mimic a real rehabilitation environment.
Within the experiments, participants were exercising their left extremity independently of their dominant one. The exercises were performed with the support or resistance of the exoskeleton with four degrees of freedom, enabling flexion/extension in hip (DOF2), knee (DOF3), and ankle joints (DOF4), and one additional rotation in the hip joint (DOF1 - abduction/adduction or internal/external rotations combination dependent on the flexion, in the same joint, DOF2). The device was either operated manually or worked automatically. All the experiments were performed with the use of a setup presented in Figure 2.
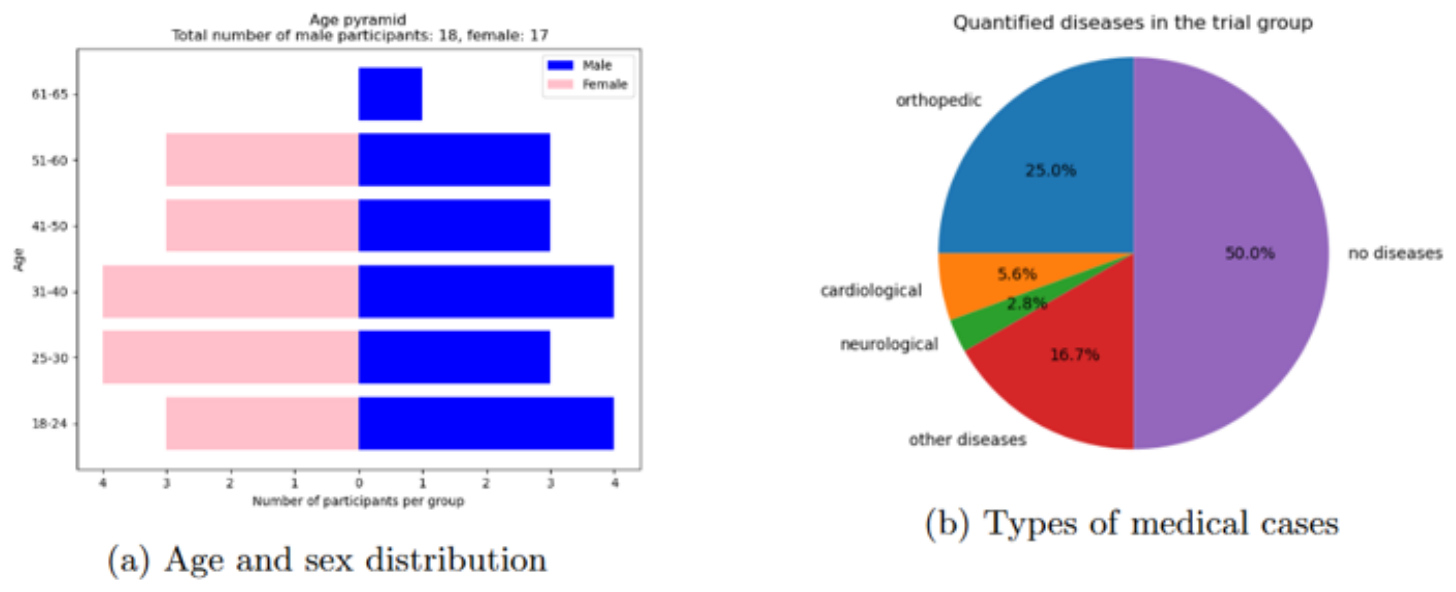

Fig. 2. Experimental setup including from left to right: (1) a patient setup - an active exoskeleton (A), EMG sensors (B), and EEG headset (C); (2) physiotherapist setup - VR headset (D) and hand controllers (E); (3) digital twin in VR - visual model of the exoskeleton and an extremity (F), operator’s hands visuals (G), EMG activity visuals for all the channels (H), and emotional state assessed based on the EEG measurements (I)
Each of the 35 participants underwent functional and efficiency (up & go and a 60-second single-leg stance) tests before and after the session with the robot, and their ranges of motion were measured. However, the data from these tests and measurements are not covered in this paper. This is due to the fact that the results obtained after a single training session have little diagnostic value and do not indicate the patient's actual improvement process. However, the obtained measures will be used as the reference for interpreting the planned longitudinal trials.
The robotic therapy session itself consisted of 3 modes:
mode 1: non-intelligent mode, which is just passive therapy with exoskeleton;
mode 2: intelligent mode in which the software corrected motions depending on the correctness measures of correlated muscle activation;
mode 3: manual teleoperation mode, where repetitions were performed using VR goggles and controllers by a physiotherapist following a reference phantom representation of expected motions.
Each mode consisted of seven repetitions for five motions initially manually registered by the physiotherapist, considering the ranges of motions and motion dynamics of each individual. These motions were representing activities of daily living and were considered a part of the task-oriented treatment for patients with orthopaedic and neurologic cases [33-35]. These were:
simultaneous flexion in the hip, knee, and ankle joints, followed by the return to the base position within a reverse motion (representing part of gait training);
short hip flexion with simultaneous knee extension, followed by the return to the base position within the shortest motion path (representing pushing objects with the foot - e.g., blocking the door);
hip circumduction - hip flexion with simultaneous knee flexion until reaching 90o by both, followed by hip abduction by 90o, followed by hip flexion with simultaneous knee extension by 90o each, followed by internal hip rotation by 90o (for increasing global range of hip motion);
hip extension until reaching 90o with simultaneous knee flexion, followed by extension in the same hip extension motion, followed by the return to the base position within the shortest motion path (representing kicking and particularly strengthening quadriceps femoris);
hip internal rotation followed by external rotation (representing wiping the floor with a wipe under the foot and strengthening hip rotators).
For all repetitions, four degrees of freedom positions were collected along with data from eight EMG sensors, and the emotional state of the patient based on the EEG data. Surface EMG sensors were placed on eight muscular groups acting as either agonists or antagonists for positive-direction motion of the exoskeleton's DOFs (see Table 1). The muscles' activity was assessed based on the real-life EMG level compared to the expected threshold based on the direction of motion in the correlated DOF, and the configuration of the distal body segment in the gravitational field. Simultaneously, the Emotive Epoc X headset was used for EEG measurements with the suggested placements of its electrodes. The detailed description of the software responsible for movement correction in mode 2, method of assessing correctness of muscular activation, as well as a description of the method for detecting the patient's condition (strain, pain, neutral, or happy), can be found in the complementary paper [29].
Tab. 1. Monitored muscle groups acting as agonists or antagonists (for positive direction of rotation) and assumed healthy ranges of motion for the exoskeleton joint motions (DOFs)
The results were compared with the statistical tests to confirm experimental hypotheses. Three of them were formed as follows:
intelligent mode (mode 2) allows for reducing the total time of incorrect muscular activations compared to non-intelligent mode (mode 1) - details and results in subsection 3.1;
EMG activation during VR mode (mode 3) is no worse than in non-intelligent mode (mode 1) - details and results in subsection 3.2;
intelligent mode (mode 2) allows for increasing the share of demanding exercises compared to non-intelligent mode (mode 1) - details and results in subsection 3.3.
All hypotheses were related to the evaluation of the measured data. The methodology for conducting statistical tests was selected based on the decision chain presented in the Figure 3. Each test was conducted for two groups (modes), considering one type of data series measured for multiple participants, multiple exercises, and multiple repetitions. Statistical significance level was equal for all cases: 0.05 [36], and the tests were performed using Python scipy.stats package. If the returned p-value was higher than the significance threshold, the H0 null hypothesis was accepted. Otherwise H1 alternative hypothesis was accepted.
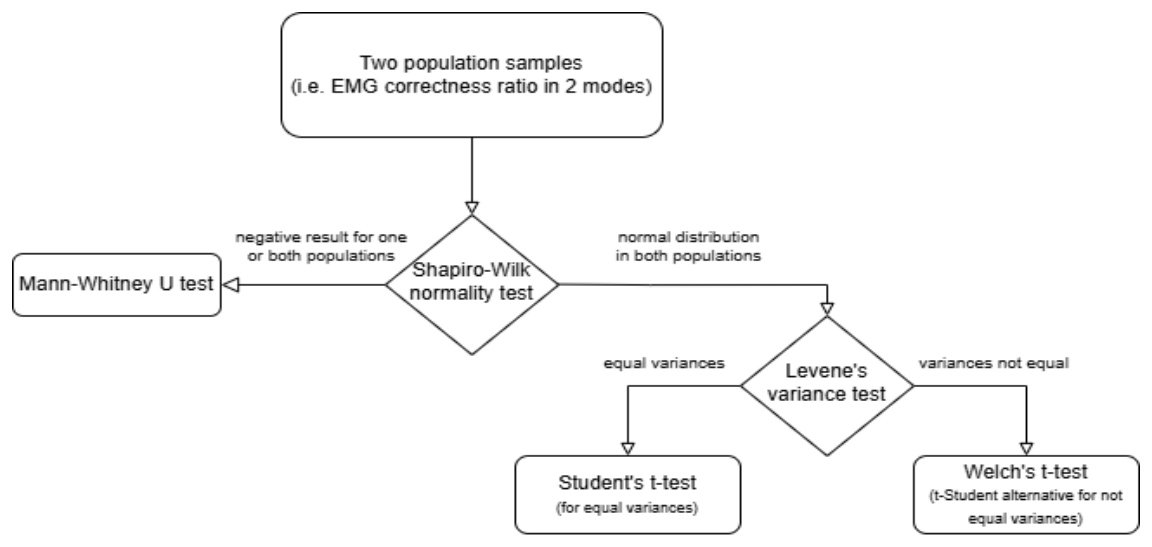
The movement to the exoskeleton was recorded in accordance with the patient's level of fitness, but the introduced speeds were similar. This makes the distribution of robot dynamics data strongly right-skewed, which is confirmed by the Shapiro-Wilk normality test. Nevertheless, the distributions of the compared groups were similar. Therefore, all comparisons of means based on the Mann-Whitney U test [37].
Following the main tests of the impact of the treatment on a participant, four additional motion accuracy tests were performed. These were aimed at comparing the obtained and set joint trajectories within the passive mode. The general methodology for calculating inaccuracies was as follows:
trajectories were shifted by the values from the cross-correlations to mitigate delays;
absolute errors were calculated for each repetition for each degree of freedom.
For each test, the median, mean, and standard deviation of the mean absolute error were computed.
RESULTS AND DISCUSSION
Test on reducing incorrect muscle activations in intelligent
According to the section 2, three statistical tests were calculated to evaluate project hypotheses. First test can be considered as proving that in intelligent mode, there is a lower ratio of incorrect activation than in the non-intelligent mode. For statistical purposes, the statistical hypotheses were stated as follows:
H0: share of incorrect muscle activity during non-intelligent training (mode 1) and intelligent mode (mode 2) are equal
H1: share of incorrect muscle activity during non-intelligent training (mode 1) and intelligent mode (mode 2) are not equal
Two populations were considered:
Population 1: incorrect shares of muscle activity during non-intelligent mode
Population 2: incorrect shares of muscle activity during intelligent mode
Both populations are not normally distributed. This leads to calculating the Mann-Whitney U test. The test statistic was U = 48,628,959.5, and the p = 1.2e-05, which rejects the H0 hypothesis, so the populations are not equal. An additional test has been calculated to prove which population is greater in that case. Hypotheses were stated as follows:
H0: shares of incorrect muscle activity during non-intelligent training (mode 1) and intelligent mode (mode 2) are lower than or equal in different repetitions
H1: shares of incorrect muscle activity during non-intelligent training (mode 1) are greater compared to an intelligent mode (mode 2) in different repetitions
The calculated statistic was U = 48,628,959.5, with the p = 6.11e-06, which rejects the H0 hypothesis and implies that the share of incorrect activations during mode 1 is greater than in mode 2. The final conclusion is that the developed automation based on EMG analysis [29] statistically lowers the number of samples with EMG incorrect activation in intelligent mode. Therefore, the use of the presented intelligent mode is beneficial for a user tending to activate muscles correlated with motions supported by the exoskeletons at an adequate level, combining conventional and cognitive muscular therapy with biofeedback [38,39].
Test on increasing share of correct muscle activations in VR mode
This test was aimed at investigating the relationship between correct muscle activations during rehabilitation using the VR mode compared to the non-intelligent mode. For statistical purposes, the statistical hypotheses were stated as follows:
H0: share of correct muscle activity during VR control (mode 3) is lower or equal compared to the share of correct muscle activity during non-intelligent training (mode 1)
H1: share of correct muscle activity during VR control (mode 3) is significantly greater than the share of correct muscle activity during non-intelligent training (mode 1)
The hypothesis analysis was simplified to a single step compared to the previous test. However, it can also be analysed step by step as presented beforehand. Test populations were considered as:
Population 1: shares of correct muscle activity during VR mode (mode 3) in different repetitions
Population 2: shares of correct muscle activity during non-intelligent mode (mode 1) in different repetitions
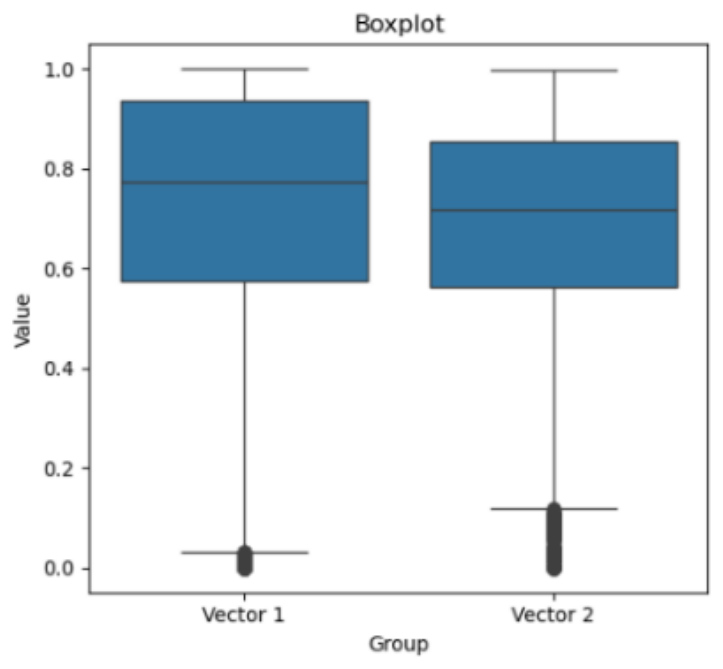
Both populations are not normally distributed. This leads to calculating the Mann-Whitney U test. The statistics is U = 48,421,185.0, and the p = 6.25e-49, which rejects H0 hypothesis. A boxplot of both populations is presented in Figure 4.
The final conclusion is that the project hypothesis regarding the correctness of EMG activation during VR mode was accepted. Therefore, it can be assumed that a physiotherapist controlling the motion through the VR system with constant feedback on the patients' muscular activation, intuitively performs the motions to encourage correct activation. In case of ineffective motions, the specialist can change the path to get better results. For this reason, it is worth implementing such control possibility into the systems for minimally supervised distant physiotherapy [18]. Such a functionality will be particularly beneficial after automatic emergency stops of the machines, after detecting abnormal muscular contractions, or while the patient will not activate muscles effectively enough [29].
However, it is worth considering that the VR mode also resulted in motions with slightly lower dynamics. Therefore, the muscles worked more freely and were engaged longer than in the case of a faster movement in non-intelligent mode. For this reason, the therapy motions aided with teleoperated robots can be expected to be slower than the ones recorded onsite with the physical device.
Test on increasing the share of demanding exercises in the intelligent training mode
This test was performed to confirm whether the intelligent mode increases the patient's perception that the exercise is demanding. This assessment was based on the EEG-based detection of emotional state assigned to the demanding exercises (strain state) [29]. The shares of such states detected within every exercise repetition were compared for non-intelligent mode (mode 1) and during control via VR (mode 3). For statistical purposes, the statistical hypotheses were stated as follows:
H0: shares of physically demanding exercises in non-intelligent mode (mode 1) and in VR control (mode 3) are equal
H1: shares of physically demanding exercises in non-intelligent mode and in VR control are not equal
Test populations were considered as:
Population 1: strain state shares during non-intelligent mode (mode 1) for every repetition
Population 2: strain state shares during VR control (mode 3) for every repetition
Firstly, H0 was rejected with statistics U = 711,081, and p = 0.002. Therefore, an additional test with alternative hypothesis H1 was performed. It showed that Population 1 is significantly greater than Population 2, rejecting the H0 hypothesis with p = 0.0008. However, based on the high medians for both populations, it can be assumed that most of the repetitions were physically demanding for the patients.
In summary, the main conclusion is that both mode 1 and mode 3 are physically demanding according to the EEG emotion detection. However, mode 3 statistically decreased the share of demanding exercises. This can be a result of the patient strain states detected due to the psychological stress during the use of mode 1. This is relatively probable, as the mode 1 repetitions were always performed prior to the mode 3. Therefore, patients were not as familiar with the motions as during the further stages. Moreover, they were not used to the robot support as much as during the later repetitions. Nevertheless, patients did not report such conscious stress.
Although the hypothesis was rejected, the results of detecting demanding exercises are satisfactory and indicate the patient's correct engagement during exercises with the robot.
Motion accuracy assessment results
After the validation of three main hypotheses, the accuracy in following recorded motions was validated. The first and second tests focused on the trajectory accuracy during mode 1 (non-intelligent mode) and mode 2 (intelligent mode). Mean absolute errors were calculated as the difference in the angular position set by the main controller and the position recorded by the encoders. The trajectories were synchronized in time with one another by shifting one of them by the extreme value of the signals' convolution. Results were analysed for every rotational joint of the exoskeleton (DOF) separately. The results are presented in the Table 2 for test 1, and in the Table 3 for test 2.
Tab. 2. Mode 1 accuracy test (test 1)
| DOF | Median [deg] | Mean [deg] | Std deviation [deg] |
|---|---|---|---|
| 1 | 0.773 | 2.603 | 3.111 |
| 2 | 0.623 | 0.670 | 0.891 |
| 3 | 1.101 | 1.905 | 2.978 |
| 4 | 0.757 | 1.397 | 2.000 |
Tab. 3. Mode 2 accuracy test (test 2)
| DOF | Median [deg] | Mean [deg] | Std deviation [deg] |
|---|---|---|---|
| 1 | 1.070 | 3.101 | 4.268 |
| 2 | 0.467 | 0.577 | 1.305 |
| 3 | 0.797 | 1.615 | 2.613 |
| 4 | 0.733 | 1.329 | 1.979 |
The results demonstrate very high accuracy in motion following, especially for robots interacting physically with humans [40]. The highest average inaccuracies occur in DOF 1 (hip abduction/adduction combined with external/internal rotation) and DOF 3 (knee flexion/extension). Inaccuracies in the former joint are the result of a different, more comfortable patient position during independent repetitions with the robot, compared to the reference motion recording. Moreover, it was observed that the latter joint has higher inaccuracies than the others due to the characteristics of the exercises performed, especially if the foot was moving very close to the floor. Potential friction of the foot sole during motions brought additional inaccuracies into DOF 3 and 4.
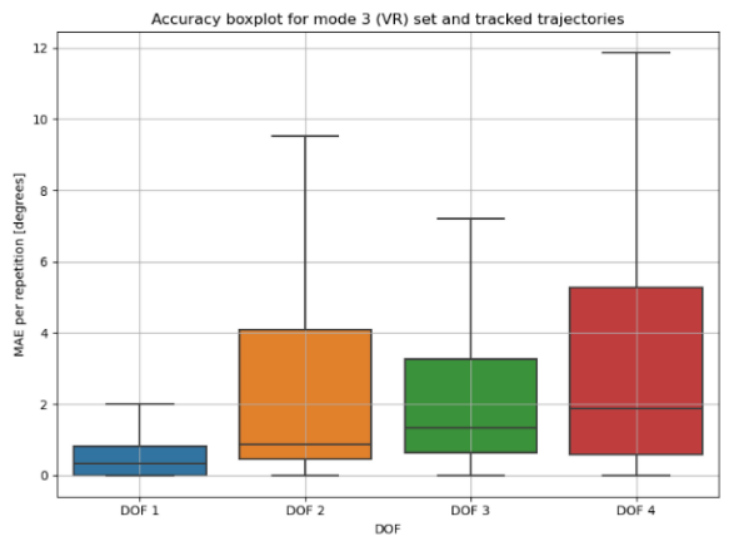
The second set of two tests investigated position accuracy in mode 3 (VR mode). Test 3 examined the accuracy of the trajectory set by the VR controllers and its mapping onto the real trajectory. The calculation technique corresponded to the one used for the first two tests. The aim of this was to verify how precise the control interference based on the digital twin in VR can be. The results are presented in Table 4 while the data boxplot is visualised in Figure 5a. In general, the quality of control was visibly lower than in the non-intelligent mode. However, the errors typically did not exceed 5 degrees, where their median remained in the range of 1-2 degrees. Such results are fully acceptable for the analysed case of telerehabilitation, especially considering the potential accuracy of alternative control signals [18,41].
It was observed that the physiotherapist operating in virtual reality gained experience in operating the robot with each session. The highest average inaccuracies were recorded for the ankle flexion/extension (DOF 4) - responsible for orientation for the most distal segment of the exoskeleton's kinematic chain. This could result from the backdrivability of the corresponding drive and the least interest in controlling this segment, as it is often preferable to remain comfortable for the patient rather than fully controlled [42].
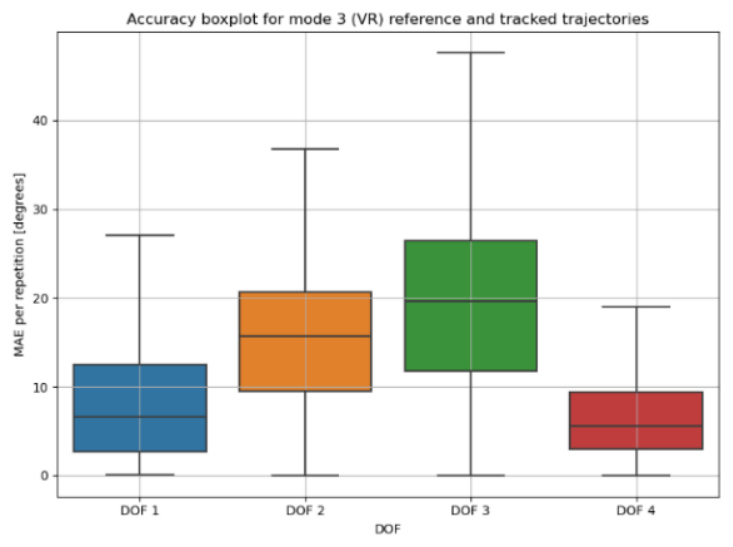
Test 4 aimed to verify how accurate the rehabilitation performed via the VR-based digital twin is compared to the reference trajectory. Therefore, it was a check of how accurately a physiotherapist can execute fully-planned movements with a robot. For this experiment, the reference trajectory was overlayed on a digital twin in VR as a semi-transparent phantom of the extremity. The physiotherapist was trying to follow the phantom with the digital twin of the exoskeleton and the extremity coupled with their physical representations in the control loop. The obtained real-life motion trajectories were compared with the reference trajectories to compute inaccuracies, as in all three previous tests. Results of this analysis are presented in Table 5 and the boxplot in Figure 5b.
Tab. 4. Inaccuracies computed within test 3
| DOF | Median [deg] | Mean [deg] | Std deviation [deg] |
|---|---|---|---|
| 1 | 0.328 | 0.574 | 1.144 |
| 2 | 0.876 | 0.574 | 6.186 |
| 3 | 1.336 | 3.544 | 6.318 |
| 4 | 1.880 | 5.134 | 8.699 |
Tab. 5. Inaccuracies computed within test 4
| DOF | Median [deg] | Mean [deg] | Std deviation [deg] |
|---|---|---|---|
| 1 | 6.636 | 8.258 | 6.553 |
| 2 | 15.684 | 14.848 | 8.823 |
| 3 | 19.59 | 18.596 | 11.384 |
| 4 | 5.554 | 6.882 | 5.749 |
The inaccuracies from test 4 are the highest compared to the previous cases. The most distal and proximal degrees of freedom (1 and 4), less involved in the test motions, have the best results, while the ones engaged more - knee and hip flexion/extension - have errors exceeding 10 degrees.
Nevertheless, the errors were decreasing while operating the system. Therefore, it can be expected to minimize them by educating physiotherapists and medics in the field of using a VR environment, becoming more common [43]. Moreover, test 3 presented that the system is capable of performing control with the fully acceptable accuracy, which should be the target of the mentioned minimization.
To contextualise the reported errors, the recorded motion trajectories span within the range of 30–90° per joint depending on the exercise type and the individual participant’s range of motion for the primary therapeutic joints (DOF2: hip flexion/extension; DOF3: knee flexion/extension). It is assumed that the whole set of experimental exercises covers the full range of mobility for a participant. The precise values for every joint for a healthy participant are presented in Table 1.
Resultant mean absolute errors of approximately 0.67° and 1.9°, respectively, in Mode 1 correspond to relative errors below 6% of full motion amplitude, which is acceptable for the application in human-interactive rehabilitation robots. The elevated errors in DOF1 are primarily attributable to the difference in resting patient posture between the reference-recording session and the therapy session, rather than to control or actuator limitations. Errors in DOF3 and DOF4 are partly attributable to foot–floor friction during exercises in which the foot approaches the ground surface.
Assessment of safety functionality for extreme cases
Separate research on emergency systems was performed, both for EMG and EEG signals, triggering the stop. In order to provide maximum safety for the patient using the exoskeleton, it was decided to implement the entire service of EMG-based muscle contraction detection and EEG-based pain recognition in the local electrical components at the patient’s side (Raspberry Pi microcomputers - RPi) of the robotic system. In case of performing remote rehabilitation, a VR operator sees the corresponding messages of detected emotional states and muscle contractions. Additionally, a critical message appears upon cramp or pain detection. When any of the conditions indicating patient hazards (cramp or pain) are detected, the robot's emergency procedure is immediately initiated.
Data from the EEG headset and EMG sensors are recorded and stored by the database server hosted on the RPi located in the electrical cabinet of the exoskeleton. If any of these signals indicate the prediction of soon-to-be pain or cramp [29], an emergency interruption flag is immediately sent to the main control computer to stop exercise. All devices are located in the patient's location, ensuring minimal delays, which is 1 ms via Ethernet cables. For the safety system trials, both cramp and pain states are triggered randomly during trials with the electrical signals emulating real-life muscular or brain activation.
Firstly, safety test was conducted for simulated spastic cramps. For this, ten sessions of cramp detection have been performed. They were detected by analysing the first derivative of EMG signals registered for every muscle separately. The cramp was assumed as potentially possible while the individual threshold was exceeded for the defined time. Every measured delay between detecting a cramp by the RPi controller and the robot stop has been presented in the Table 6. It was assumed that the additional delay of measuring and processing the EMG was not bigger than 100 ms in total (based on the setup frequency) [29].
Tab. 6. Times of critical events (at their end) during trials of the cramp detection
The cramp detection formula is based on the backward differentiation formula (also known as the backward Euler method). If a relatively high EMG value is registered, compared to the previous one, and if the value of the derivative is higher than a threshold, the safety procedure is activated. Delays are calculated as a D-C column timestamp subtraction (see Table 6). All the registered delays were lower than 25 ms. This value was relatively low compared to the time of computation and measuring the signals. That was possible to achieve only by handling the security procedure locally, which maximizes the safety and robustness of the system.
Then, ten sessions of pain detection have been performed. The pain states detected based on bandwidths from selected frontal lobe electrodes were reflecting the states in which there is a high risk of real pain appearing within two seconds [29]. Every measured delay between receiving information about a pain state by the RPi controller and activating the emergency state has been presented in the Table 7. It was assumed that the additional delay of measuring and processing the EEG was not bigger than 2 s in total (based on the setup frequency) [29].
Tab. 7. Times of critical events during trials of pain detection
All the registered delays were lower than 45 ms. Like for cramp detection, this value was relatively low compared to the time of computation and measuring the signals. The reaction to risks detected by the EMG and EEG signal was very fast and met the design assumptions for the SmartEx-Twin exoskeleton. Therefore, they are applied to the final design of the system.
Study limitations
Several limitations should be considered. First, the cohort was intentionally heterogeneous, spanning healthy volunteers and participants with neurological, orthopaedic, cardiological and undiagnosed conditions across a wide age range. This composition reproduces a realistic rehabilitation setting, but the subgroups were too small to support a stratified analysis. The pooled comparisons, therefore, cannot attribute effects to specific conditions, and the results should be read as a feasibility-level characterisation across a mixed population rather than as condition-specific evidence.
Moreover, all teleoperation was performed by a single physiotherapist whose accuracy did not improve at the statistical level over the course of the study. Nevertheless, it is possible that various operators can perform with changing performance, what should be considered in the planned longitudinal continuation of the investigation.
CONCLUSIONS
The investigation was conducted to prove the effectiveness and the safety of the developed intelligent system for exoskeleton-aided physiotherapy. Apart from the intelligent systems automating the therapy, distant VR-based teleoperation was also tested. Thanks to this, an operator could have taken over control of the device remotely, which was critical to manage emergency scenarios. The trials were divided into three types:
Validating the effectiveness of an intelligent mode, and the distant control via VR;
Control accuracy during different modes, also including the VR-based control;
Testing reaction time of provided safety systems for spastic cramp detention and identifying risk of patients' pain.
Within the tests, it was proven that the intelligent mode results in better muscular activation than the non-intelligent mode, while VR-based control results in better muscular activation than the non-intelligent mode, but does not increase the level of perceiving these as physically tiring. The accuracy of control for different modes was also assessed as very accurate. However, digital-twin-based teleoperation brought additional inaccuracies. These depended mainly on the operators' skills in using VR, as adding the VR environment itself into the control chain did not increase the inaccuracies to an unacceptable level. Moreover, the safety systems responded with 100% accuracy to the modelled triggers, and the system launched the emergency stop mode within the assumed times.
Due to this, the presented method of intelligent algorithms for automating and supervising exoskeleton-aided therapy was assessed as effective and safe. It was implemented into the SmartEx-Twin exoskeleton developed in Łukasiewicz-PIAP institute. However, the method is applicable universally to the exoskeletons and can be transferred to the end-effector robots. The former requires only defining the muscular groups corresponding to the exoskeleton's joints and implementing expected activations into the assessment algorithm. The latter required more invasive modification of the algorithm itself. Nevertheless, both cases are applicable to use the methodology itself. Regarding EEG measurements, the use of other devices can require building a new emotion-recognition model, as the motions can also affect the accuracy of the obtained signals.
In the future, the system of teleoperation will be further investigated to shorten the control-loop delays and minimize inaccuracies coming from operating the VR-based environment. The planned continuation as longitudinal experiments will focus on heterogeneous groups of neurological and orthopaedic patients to confirm the functional effects of the therapy for specific medical conditions.

